
Private Urogynaecology Specialists · Chelsea, London
Private Bladder & Prolapse Care
Consultant-led
Chelsea Clinic
Consultant-led assessment and treatment for bladder, pelvic floor and prolapse problems. Examination, scan and a clear treatment plan, usually in a single visit.
- Urgent appointments available, no GP referral needed
- Seen by a consultant urogynaecologist at every appointment
- Bladder and pelvic floor assessment at the same visit
- Non-surgical options first, surgery only if you need it
- Self pay and all major insurers welcome
★★★★★
4.9/5 on  Google &

Trusted by women across London
Google & Trusted by women across London
Self Pay & Insurance Welcome





Understanding Urogynaecology
What Is Urogynaecology?
Urogynaecology is the specialty that looks after the bladder, the pelvic floor and the support structures that hold the pelvic organs in place. It covers urinary leakage, an overactive bladder, pelvic organ prolapse, recurrent urine infections and the pelvic changes that often follow childbirth or the menopause.
Around one in three women will experience urinary leakage at some point in her life, and many more live with a prolapse they have never mentioned to anyone. These problems are common, they are not something you have to accept as part of getting older, and in most cases they improve considerably with the right treatment.
Symptoms We See Every Week
If any of the following sound familiar, a consultant assessment can give you answers:
- Leaking when you cough, sneeze, laugh or exercise
- Sudden urgency, or not making it to the toilet in time
- Going to the toilet very often, or waking at night to go
- A bulge, heaviness or dragging feeling in the vagina
- Difficulty emptying your bladder or bowel completely
- Repeated urine infections, or infection-like symptoms
- Discomfort or dryness during sex, or reduced sensation
- Pelvic symptoms that started after childbirth or the menopause
★★★★★
“The entire team are very knowledgeable, personable, so friendly and thorough in everything they do, which made me feel like I was in the best possible hands.”
Verified Doctify review, June 2026
What We Treat
Typical Urogynaecology Conditions
Bladder and pelvic floor problems rarely come on their own. Your consultant will look at the whole picture rather than treating one symptom in isolation.
Bladder control
Urinary Incontinence
Leakage on coughing, laughing or exercising (stress incontinence), leakage with sudden urgency (urge incontinence), or a combination of the two.
- Stress, urge and mixed incontinence
- Overactive bladder and night-time waking
- Leakage after childbirth or the menopause
Pelvic support
Pelvic Organ Prolapse
When the bladder, womb, bowel or vaginal walls drop from their usual position, causing a bulge, heaviness or a dragging sensation.
- Bladder (anterior) and bowel (posterior) prolapse
- Uterine and vaginal vault prolapse
- Graded and explained clearly at your visit
Recurrent infections
Recurrent UTIs & Bladder Pain
Repeated urine infections, or bladder pain and urgency with no infection found. Both need proper investigation rather than another course of antibiotics.
- Two or more infections in six months investigated
- Causes identified, not just symptoms treated
- Prevention plan tailored to you
After childbirth
Postnatal Pelvic Floor Problems
Pelvic floor weakness, leakage, prolapse or perineal problems following birth, including symptoms that appeared years afterwards.
- Assessment of pelvic floor strength and injury
- Bladder and bowel control after birth
- Rehabilitation plan and physiotherapy referral
Hormonal change
Menopause Pelvic & Bladder Symptoms
Falling oestrogen thins the tissues of the vagina, urethra and bladder, causing dryness, urgency, discomfort and repeated infections.
- Genitourinary syndrome of the menopause
- Vaginal dryness, soreness and urgency
- Local oestrogen and non-hormonal options
Bowel symptoms
Bowel Control & Emptying
Difficulty controlling wind or stool, or trouble emptying the bowel, is a pelvic floor problem as much as a bowel one and is treated as such.
- Faecal urgency and leakage assessed
- Incomplete emptying and straining
- Joint care with colorectal specialists where needed
Getting a Diagnosis
How We Assess Bladder & Prolapse Symptoms
Getting the diagnosis right matters, because stress incontinence, an overactive bladder and prolapse are treated very differently. Most of the assessment happens at your first visit.
01
Step one
Specialist Consultation
An unhurried appointment with a consultant urogynaecologist covering your symptoms, births, medication, bowel habit and how all of it affects your daily life.
02
Same visit
Pelvic Floor Examination
A gentle examination to grade any prolapse, assess pelvic floor muscle strength and check the tissues of the vagina and urethra.
03
Often same visit
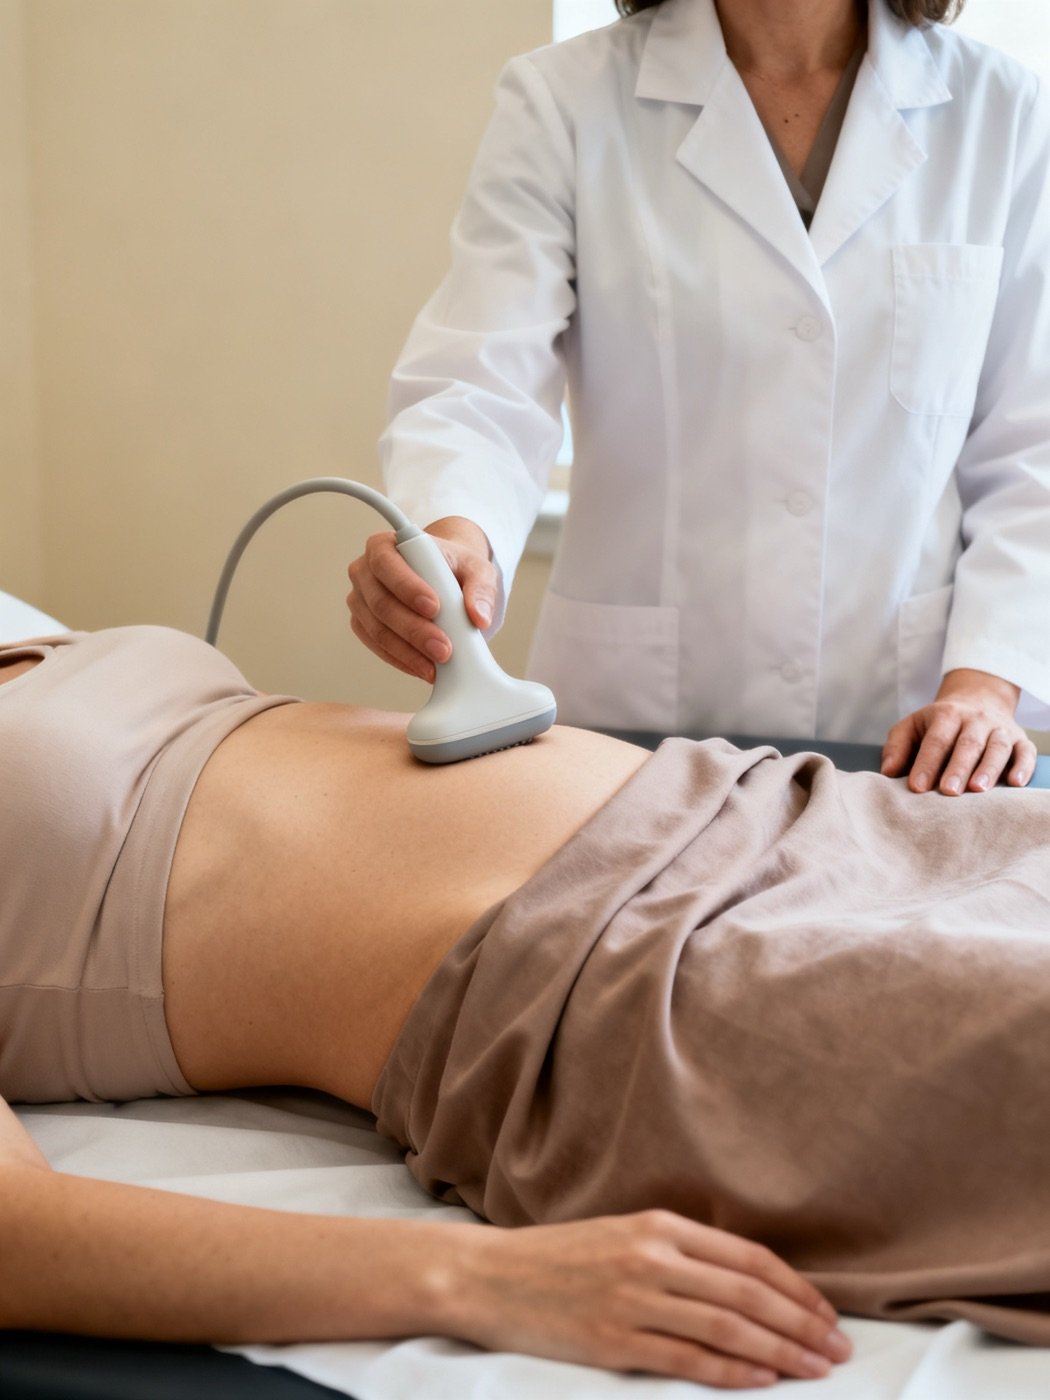
Pelvic Ultrasound
A specialist scan of the womb, ovaries and bladder, including how well your bladder empties, to rule out other causes of your symptoms.
04
Simple tests
Urine Testing & Bladder Diary
Urine testing to exclude infection, plus a short bladder diary that shows exactly what your bladder is doing across a normal few days at home.
05
Where needed
Urodynamic Studies
A detailed test of bladder pressure and function, arranged when symptoms are mixed or unclear, or before any decision about continence surgery.
06
Your plan
A Clear Diagnosis
You leave knowing what is causing your symptoms, what your options are, and which one your consultant recommends starting with and why.
Your Treatment Options
Treatment Built Around What You Actually Need
Most women improve significantly without an operation. Your consultant will always start with the least invasive option that is likely to work for your symptoms.
First-line treatment
Pelvic Floor Rehabilitation
Supervised pelvic floor muscle training is the recommended first treatment for stress incontinence and mild prolapse, and it works for a great many women.
- Referral to specialist pelvic health physiotherapy
- A programme of at least three months
- Progress reviewed with your consultant
Non-surgical
Vaginal Pessary Fitting
A pessary is a small, soft support fitted inside the vagina to hold a prolapse in place. It is fitted in clinic, works immediately and avoids surgery altogether for many women.
- Fitted and checked at your appointment
- Several types and sizes available
- Routine changes and reviews arranged
Overactive bladder
Bladder Retraining & Medication
For urgency and frequency, structured bladder retraining combined with medication where appropriate can substantially reduce how often you need to go.
- Bladder retraining programme
- Medication reviewed for side effects and fit
- Fluid and lifestyle adjustments that actually help
Hormonal support
Vaginal Oestrogen & Menopause Care
Local vaginal oestrogen restores the tissues around the bladder and urethra. It often improves urgency, dryness and recurrent infections, and can be used alongside HRT.
- Local treatment with very low systemic absorption
- Non-hormonal alternatives where preferred
- Joined-up care with our menopause consultants
Minimally invasive
Continence Procedures
Where conservative treatment has not worked, day-case procedures such as urethral bulking injections can improve stress incontinence with a short recovery.
- Urethral bulking injections
- Bladder injections for severe urgency
- Risks and benefits explained fully first
Surgical options
Prolapse & Continence Surgery
If surgery is the right answer, your consultant will talk you through each option, what it involves, what the recovery looks like and what current national guidance says.
- Vaginal prolapse repair procedures
- Uterine-preserving options where suitable
- Continence surgery discussed in full
GMC Registered Consultants
CQC Regulated Clinic
All Major Insurers Accepted
274 Fulham Road, Chelsea
Consultant-Led Scanning
Transparent Pricing
Clear Prices, No Hidden Costs
All prices are per appointment. Your final fee will depend on your clinical needs. All major health insurers are welcomed.
Initial Consultation
A thorough one-to-one assessment of your bladder, bowel and pelvic floor symptoms with a consultant, including a clinical examination.
- With a GMC-registered consultant
- Full symptom and birth history review
- Pelvic floor examination included
- Written care plan and next steps
£300
Consultation & Scan
The most complete first visit. A full consultation with a consultant plus a specialist pelvic ultrasound, all in a single appointment.
- Initial consultation with a consultant
- Specialist pelvic ultrasound scan
- Checks how well your bladder empties
- Immediate results and full care plan
£475
Follow-Up Appointment
To review your results, refine your treatment plan, check a pessary or see how you are getting on after a procedure.
- With the same consultant throughout
- Results review and treatment planning
- Pessary check and post-procedure review
- Referral letters and onward care
£260
Your Specialists
Meet Your Urogynaecology Team
Every appointment is with a named consultant who specialises in urogynaecology. You will see the same specialist from your first visit through to treatment.

Dr Dina El-Hamamsy
Consultant Gynaecologist, Specialist in Urogynaecology
Specialist in urogynaecology and pelvic health, caring for women with urinary incontinence, pelvic organ prolapse, recurrent urine infections and pelvic floor problems after childbirth and the menopause.

Raman Basra
Consultant Urogynaecologist
Consultant urogynaecologist with a specialist interest in bladder function, incontinence and prolapse, from conservative treatment and pessary care through to surgical management. GMC: 6053269
Why Choose Ovara Health?
a
Consultants Only
a
Independently Regulated
a
Urgent Appointments Available
a
Everything Under One Roof
Your Questions
Frequently Asked Questions
What does a urogynaecologist do?
A urogynaecologist is a consultant gynaecologist with specialist training in the bladder, the pelvic floor and the support of the pelvic organs. They diagnose and treat urinary incontinence, overactive bladder, pelvic organ prolapse, recurrent urine infections, bowel control problems and pelvic floor damage after childbirth. Treatment ranges from physiotherapy, pessaries and medication through to surgery where it is needed.
Do I need a GP referral to see a urogynaecologist?
No. You can book directly as a self-pay patient without a GP letter or referral. If your insurer requires a referral for pre-authorisation, our reception team can help you arrange that before your appointment.
What happens at a urogynaecology appointment?
Your consultant will take a full history covering your bladder, bowel and pelvic symptoms, your births and any previous surgery. With your consent there is a gentle pelvic examination to grade any prolapse and assess pelvic floor strength, and a urine sample is tested. A pelvic ultrasound is often carried out at the same visit. You will usually leave with a diagnosis and a treatment plan on the day.
Can urinary incontinence be treated without surgery?
In most cases, yes. Supervised pelvic floor muscle training is the recommended first treatment for stress incontinence and helps a large proportion of women. For urgency and frequency, bladder retraining and medication are usually tried first. Vaginal oestrogen can help considerably after the menopause. Surgery is only considered when these options have been given a proper trial.
What is a vaginal pessary and does it hurt?
A pessary is a small, soft, flexible device fitted inside the vagina to support a prolapse. Fitting is done in clinic and should not be painful, though it can feel odd for a moment. Once the right size and type are in place you should not feel it at all. Many women use a pessary for years and avoid surgery entirely. It is checked and changed at routine appointments.
Is a prolapse dangerous?
A prolapse is not usually dangerous, but it can be uncomfortable and can affect your bladder, bowel, exercise and sex life. It is graded by how far the organ has descended. Mild prolapse often improves with pelvic floor physiotherapy and lifestyle changes. More advanced prolapse may need a pessary or surgery. Getting it assessed early gives you more options, so it is worth having it looked at rather than waiting.
Why do I keep getting urine infections?
Recurrent urine infections, usually defined as two or more in six months or three or more in a year, often have an underlying cause. Incomplete bladder emptying, prolapse, thinning of the tissues after the menopause or an ongoing low-grade infection can all be responsible. A urogynaecology assessment looks for the cause rather than treating each infection separately, and builds a prevention plan around what is found.
Are these problems just part of getting older or having children?
They are common after childbirth and around the menopause, but common is not the same as normal or untreatable. Leaking, urgency and prolapse all respond well to treatment at any age. Many women manage symptoms quietly for years before seeking help and are surprised at how much can be done in a short space of time.
How quickly can I be seen?
Most patients are offered an appointment within 48 hours of getting in touch. No GP referral is needed. You can book directly by phone, email or by completing the form below.
How much does a private urogynaecology consultation cost?
An initial consultation with a consultant is £300. A consultation combined with a specialist pelvic ultrasound, which is the most comprehensive first visit option, is £475. Follow-up appointments are £260 and fitting a vaginal support pessary is £856. Urodynamic studies and surgical fees are quoted individually after your consultation. All major health insurers are accepted.
Find Us
Our Chelsea Clinic
Address
274 Fulham Road, Chelsea, London SW10 9EW
Phone
Opening Hours
Monday to Friday: 8am to 6.30pm
Saturday: 9am to 5pm
Sunday: Closed
Getting Here
Nearest tubes: Fulham Broadway (District) and South Kensington (District, Circle, Piccadilly). Street parking and buses available.

Book Your Appointment
Ready When You Are
Call us now, or leave your details and our reception team will call you back the same working day to confirm a time.
-
Call us020 7751 4488
Mon to Fri 8am to 6.30pm, Sat 9am to 5pm -
Email usreception@ovarahealth.co.uk
-
Visit us274 Fulham Road, Chelsea, London SW10 9EW
-
Insurance welcomeBupa, AXA, Aviva, Vitality, WPA, Cigna